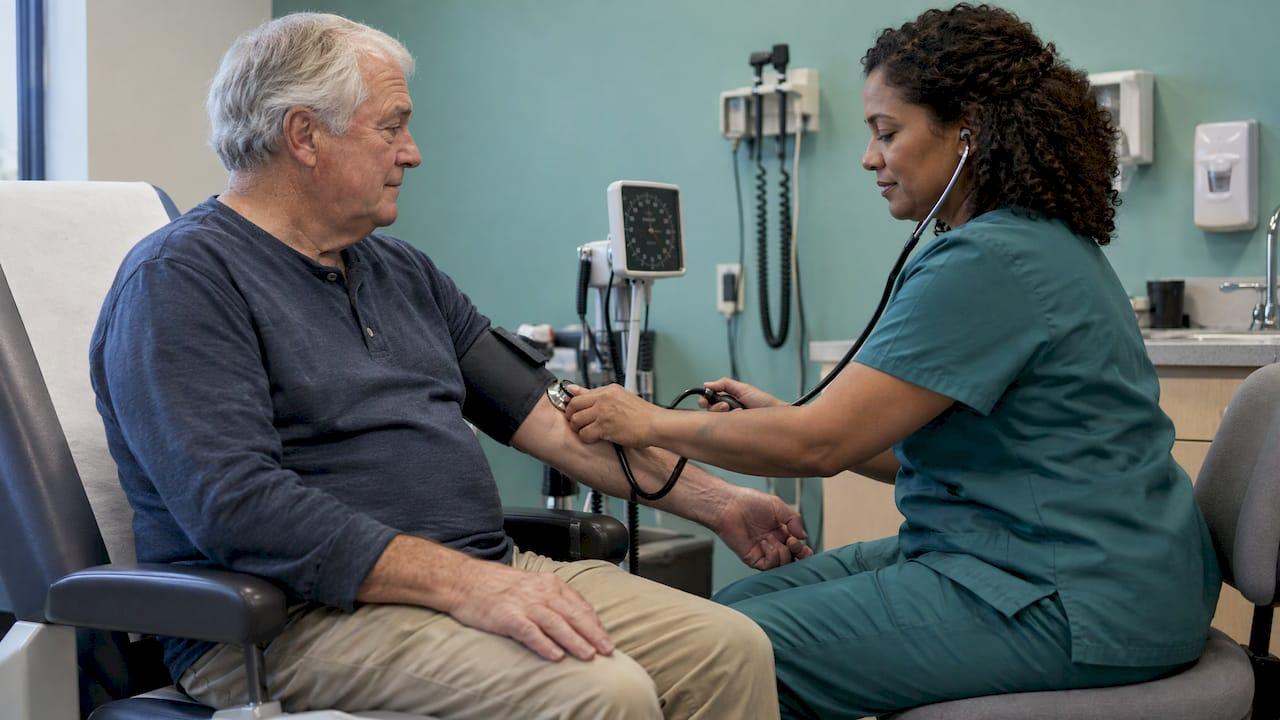
Detox for an older adult should be medically supervised, and for most people over 65 that means round-the-clock monitoring rather than stopping at home. Age changes how the body handles alcohol, benzodiazepines and opioids, and withdrawal can turn dangerous at lower levels of use than families expect. This guide explains why, what a safe detox looks like, and what should come after it.
TL;DR
- Older adults can have serious withdrawal even after a moderate daily intake, and patients 65 and older face a higher risk of complications because of other illnesses, longer drinking history and greater sensitivity to treatment.
- Most elderly patients with withdrawal symptoms should be considered for inpatient care, with outpatient detox reserved for those with strong support and no complicating factors.
- Clinicians usually start with lower doses and shorter-acting medications in this age group, and they adjust as the person responds.
- Severe shaking, seizures, hallucinations or extreme confusion are emergencies: call 911.
- Detox is the first step. A plan for therapy, mental health care and aftercare is what protects the gains.
Table of Contents
- Why detox is different after 65
- Warning signs that need emergency care
- How long withdrawal lasts
- Inpatient or outpatient: where should an older adult detox?
- How clinicians adjust medications for older patients
- Treating anxiety, depression and trauma at the same time
- Perspective from our team
- What should follow detox
- How to choose a detox program for an older loved one
- Medical detox at Connected Recovery
- FAQ
- Sources
Why detox is different after 65
Aging changes the brain, liver and kidneys. Those changes make withdrawal harder to predict and harder to treat. A review of delirium tremens in older adults notes that patients 65 and older are at increased risk of withdrawal complications. The reasons it gives are more co-existing conditions, including cognitive impairment, a longer drinking history, and a greater sensitivity to the drugs used in treatment, because the brain adapts less well to stress.
Several things combine in practice:
- Lower thresholds. Canada's Centre for Addiction and Mental Health notes that withdrawal needing treatment is rare below about six drinks a day, except in older adults, who may develop significant symptoms on only several drinks a day. The same page says elderly patients often have a more complicated course because of other health problems and frailty.
- Slower, longer withdrawal. A county behavioral health resource reports that acute alcohol withdrawal is more protracted and severe in older adults than in younger adults, and that detoxification may take several weeks or even months.
- Delayed recognition. Older patients often arrive at a hospital for something else, such as a fall, an infection or a heart problem. A journal review on delirium tremens in the elderly says this often delays the diagnosis and lengthens the hospital stay.
- Hidden use. Federal Bureau of Prisons guidance on opioid use disorder points out that aging patients can be harder to identify. Stereotypes, denial and age-related changes or medical conditions can mask the signs of opioid use disorder.
Alcohol is only part of the picture. Many older adults also take prescription sedatives, sleep aids or opioid pain medication, sometimes for years. Each of these has its own withdrawal pattern, and stopping any of them suddenly can be risky. If you or a parent takes a benzodiazepine every night, do not stop it alone. A planned reduction is the safer route, and our overview of benzodiazepine taper guidelines explains the usual pace clinicians use.
Warning signs that need emergency care
Mild withdrawal looks like anxiety, sweating, tremor, nausea and poor sleep. In an older person, these can slide into something dangerous quickly, and some of the signs are easy to mistake for ordinary age-related problems.
Call 911 right away for any of the following. The nonprofit Partnership to End Addiction lists severe shaking, hallucinations, seizures, extreme confusion or not knowing where they are, and significant changes in heart rate or blood pressure as reasons to contact emergency services. UK national clinical guidance adds worsening shaking with very heavy sweating and suspected Wernicke's encephalopathy to the list of situations needing an ambulance.
The stakes are real. The review of delirium tremens in the elderly describes it as a medical emergency with high mortality. It puts the range at 5 to 15 percent, most often from cardiac arrhythmias, and says the risk is likely higher in older patients.
Two practical points for families:
- New confusion is a symptom, not a personality change. If a parent becomes disoriented, agitated or sees things that are not there within days of stopping or cutting back, treat it as an emergency.
- Fluids matter. Sweating, vomiting and poor appetite can dehydrate an older person fast. This resource on dehydration in seniors covers the warning signs, and in a withdrawal setting the medical team should monitor hydration continuously rather than leaving it to chance.
How long withdrawal lasts
Timelines vary by substance, amount, health and history. For alcohol, CAMH says symptoms can begin six to 12 hours after the last drink, usually peak at two to three days, and can last up to seven days. A subacute phase with insomnia, irritability and craving may continue for weeks.

In an older adult, plan for the longer end of any range. Our hour-by-hour alcohol withdrawal timeline shows what clinicians watch for at each stage, and our piece on the first 72 hours of inpatient alcohol detox explains why monitoring is heaviest early on. Lingering symptoms after the acute phase are covered in our guide to post-acute withdrawal syndrome.
One more point on timing. Past withdrawal predicts future withdrawal. CAMH notes that people with a history of delirium tremens or withdrawal seizures are at high risk of recurrence if they drink again and then stop. That makes a first, well-managed detox worth getting right.
Inpatient or outpatient: where should an older adult detox?
The medical literature leans toward closer supervision. Kraemer, Conigliaro and Saitz, writing on elderly alcohol withdrawal, say most elderly patients with withdrawal symptoms should be considered for inpatient admission. Outpatient management may suit those with adequate social support, no significant symptoms when they present, no comorbid illness and no history of complicated withdrawal.
French alcohol society recommendations go the same direction. For vulnerable elderly patients, including those with physical disability, heavy medication use or cognitive impairment, they say a hospital-level setting is preferable to control or prevent delirium tremens, convulsions, falls and intracerebral hematomas.
A behavioral health resource citing federal treatment guidance says patients who are frail, acutely suicidal or medically unstable, or who need constant one-on-one monitoring, should receive 24-hour medical, psychiatric and nursing care in a medically managed setting.
Here is a simple way to think about it:
| Situation | Usually points toward |
|---|---|
| Heavy or long-term daily use, any past seizures or delirium tremens | Medically supervised inpatient detox |
| Several chronic conditions or many daily medications | Medically supervised inpatient detox |
| Memory problems, frailty, history of falls | Medically supervised inpatient detox |
| Depression, anxiety, suicidal thoughts alongside use | Inpatient detox with mental health care |
| Light use, no past complications, strong support at home, physician-approved plan | A physician may consider outpatient care |
This table is a starting point, not a diagnosis. A physician decides, and our guide to inpatient versus outpatient detox walks through the questions to ask. We also explain why detoxing at home without supervision is risky, and why to get medical advice before you stop.
How clinicians adjust medications for older patients
Age-adjusted dosing is the main difference between treating a 35-year-old and a 75-year-old. The following is for understanding only. The prescribing decisions belong to the treating physician.
Alcohol withdrawal. Benzodiazepines remain the standard drug class. For older adults, sources agree on caution:
- The Department of Veterans Affairs advises starting lower benzodiazepine doses for geriatric patients. It also says shorter-acting agents such as lorazepam carry less risk of accumulation when the liver's capacity to metabolize drugs is reduced.
- French recommendations favor short half-life benzodiazepines and say initial doses should be reduced by 30 to 50 percent in elderly patients.
- The delirium tremens review says long-acting drugs such as diazepam and chlordiazepoxide should be avoided in the elderly because they accumulate, and that dexmedetomidine may be used when excessive sedation is a concern.
- There is a trade-off. Short-acting options may be less effective at preventing seizures and more prone to discontinuation symptoms if not tapered properly. This is one reason continuous nursing observation matters.
- The VA also notes carbamazepine as an alternative to benzodiazepines, and that beta-blockers, phenytoin and clonidine are not considered appropriate on their own but may be added in certain patients.
Other medication options exist, and we cover two of them in plain language: phenobarbital for alcohol withdrawal and gabapentin for alcohol withdrawal.
Opioid withdrawal and treatment. Federal Bureau of Prisons guidance says no FDA-approved medication for opioid use disorder is contraindicated in elderly patients. Providers should still weigh pain, psychiatric disorders, kidney or liver problems and polypharmacy when choosing a medication. For patients 50 and older, it recommends starting buprenorphine at a lower dose and titrating more cautiously, and it flags methadone for added risk of sedation and QTc prolongation.
That is why a full medication review at admission matters. Blood pressure drugs, blood thinners, diabetes medications and sleep aids all interact with withdrawal treatment.
Treating anxiety, depression and trauma at the same time
Substance use in later life often grows out of loss: a spouse, a career, a home, health. Anxiety and depression can be both a cause and a consequence. State standards of care make the same point, noting that effective treatment attends to multiple needs of the person, not just the drug use. Our article on anxiety and alcohol explains why relief from a drink rebounds into worse symptoms, and why detox needs medical care.
Privacy is a common worry for older adults and their families, particularly people who spent a lifetime protecting their reputation. In the United States, a federal rule, 42 CFR Part 2, gives substance use treatment records strong protection. The Washington State Health Care Authority explains that it allows very limited disclosures without consent. The main exception is a medical emergency, and sharing for treatment purposes outside the program needs explicit consent. Ask any facility how it handles your records and who may be told about your stay. You decide who receives updates.
Perspective from our team
In our experience, the older people who do best in detox are the ones who are noticed. A tremor that looks like "just nerves," a night of poor sleep that looks like "just age," a brief spell of confusion: in a larger, busier setting these can pass unremarked.
That is why we keep Connected Recovery to 12 beds. With a small census, our clinical team can watch each person closely, with 24/7 medical supervision, and adjust the plan as the days go on. The research is clear that older adults need careful, individualized medication choices and close observation. A small program is built to do exactly that.
We also treat substance use and mental health together. Grief, depression, anxiety and trauma rarely wait their turn, so our dual diagnosis approach addresses them in the same plan, in a setting that feels more like a private retreat than an institution.
If you are weighing whether a parent, spouse or you yourself needs supervised detox, call us and describe the situation. We will tell you honestly what level of care the symptoms point to.
Jim
What should follow detox
Detox clears the substance. It does not treat the reasons the person was using. A behavioral health resource notes that older adults tend to be more compliant in treatment than younger adults. For late-onset problems, once any necessary detoxification is done, harm reduction may come first, closely followed by strengthening the person's social support. That is encouraging news for families.
A good plan after detox usually includes:
- Residential or structured treatment to build routines, treat mental health conditions and rebuild confidence. See our residential treatment program.
- Medication-assisted treatment where appropriate, particularly for opioid or alcohol use disorders, through our MAT program.
- Treatment of co-occurring conditions such as depression, anxiety or trauma, covered by dual diagnosis treatment.
- Aftercare and discharge planning so the person leaves with appointments, support and a relapse prevention plan. Read about our aftercare planning and discharge planning.
- Family involvement. Social connection is protective, and families can learn how to support recovery without taking over.
State standards of care stress that no single treatment fits everyone, and that a person's plan must be assessed continually and modified as needs change. A plan written for a 40-year-old will not necessarily suit a 72-year-old with heart disease and a recent loss.
The same behavioral health resource suggests that, for older people who misuse substances, the least intensive and confrontational options be explored first. It names brief intervention, intervention and motivational counseling as approaches that work either as pretreatment or as treatment. If you are a family member, a calm, caring conversation is usually a better start than an ultimatum.
How to choose a detox program for an older loved one
Use these questions when you call any facility:
- Is a medical team on site around the clock, and who assesses new symptoms at night?
- How are medication doses chosen for older patients, and is there a full review of current prescriptions at admission?
- How many patients does each nurse and clinician look after?
- Can the program treat depression, anxiety or trauma alongside the addiction?
- How are records protected, and who can be told about the stay?
- What happens after detox, and who builds the aftercare plan?
- Which insurance plans are accepted, and what are the private-pay options?
A good admissions team answers these without pressure. If a person is in withdrawal and unsafe, call 911 first and sort out placement afterward.
Medical detox at Connected Recovery
Connected Recovery is a boutique, 12-bed accredited facility in Van Nuys, Los Angeles, serving adults. Our medical detox offers 24/7 medical supervision, a tailored plan for each person, and a direct path into residential treatment, dual diagnosis care and aftercare. Admissions are private and confidential. Call or visit our website to talk through a situation and check insurance or private-pay options.
For a look at all the conditions and services we treat, see our programs overview.
FAQ
Is detox dangerous for seniors?
It can be, particularly for alcohol and sedatives. Older adults face a higher risk of complications because of other health conditions, longer use and greater sensitivity to treatment. Supervised care with continuous monitoring lowers that risk, because problems are caught and treated early.
How long does detox take for an older adult?
Acute alcohol withdrawal often peaks within two to three days and can last up to a week. In older adults it may be more drawn out, and a longer phase of poor sleep, irritability and craving can follow. The clinical team sets the pace based on symptoms, not a fixed calendar.
Can an older adult detox at home?
Some carefully selected patients with strong support, mild symptoms and no complicating history may be managed as outpatients, but only under a physician's plan. Most elderly patients with withdrawal symptoms should be considered for inpatient care. Never stop alcohol or sedatives suddenly without medical advice.
Are the medications the same as for younger adults?
The drug classes are often similar, but doses are usually lower and the choice of agent is more cautious. Clinicians prefer shorter-acting benzodiazepines for older patients and review all other medications for interactions. The treating physician decides on the exact plan.
What if my parent refuses help?
Start with a calm, private conversation focused on health and safety, not blame. Brief, motivational approaches tend to work better than confrontation with older adults. If there are seizures, hallucinations or severe confusion, call 911 regardless of consent.
Sources
- Delirium Tremens in the Older Adult (PMC)
- Alcohol Use: Managing alcohol withdrawal (CAMH)
- Delirium tremens in the elderly (International Journal of Neuropsychiatric Medicine)
- Managing alcohol withdrawal in the elderly (PubMed)
- Pharmacotherapy for Alcohol Dependence: The 2015 French Alcohol Society recommendations (PubMed)
- Seniors and substance abuse (Alameda County Behavioral Health)
- Medication Assisted Treatment for Opioid Use Disorder (Federal Bureau of Prisons)
- How to Conduct Detoxification (Department of Veterans Affairs)
- Alcohol Withdrawal Symptoms, Levels, and When to Seek Help (Partnership to End Addiction)
- Clinical guidelines for alcohol treatment: community-based medically assisted withdrawal (GOV.UK)
- Standards of Care (Massachusetts DPH)
- Sharing Substance Use Disorder Information guide (Washington State HCA)