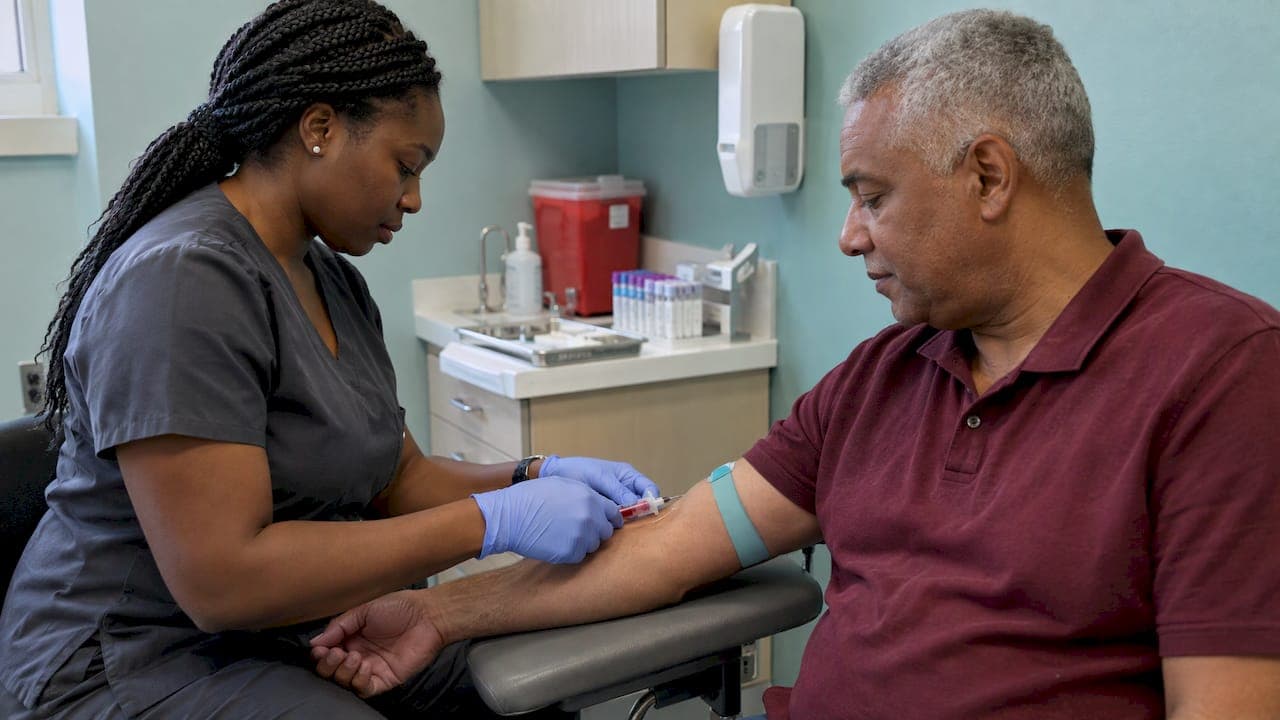
Mood stabilizers are medications that smooth out the manic and depressive swings of bipolar disorder, and in dual diagnosis they are one part of a plan that treats the mental health condition and the substance use at the same time. They are not a treatment for addiction on their own, and the research on which drug works best when both conditions are present is still limited. What helps most is a prescriber who knows your full substance history, regular monitoring, and therapy that runs alongside the medication. This guide explains what these medications do, where the evidence is thin, what changes when alcohol or drugs are in the picture, and what safe monitoring looks like.
TL;DR
- Mood stabilizers include lithium, anticonvulsants such as valproic acid, lamotrigine and carbamazepine, and some antipsychotics. They help control mania and depression and can help prevent relapse into mood episodes.
- Evidence for any single drug in people with bipolar disorder and a substance use disorder is limited, so the choice is individual and made by a prescriber who knows your substance use.
- Alcohol and other drugs can change how these medications behave. Marijuana, for example, can raise lithium levels toward a toxic range.
- Lithium needs blood tests, hydration and attention to warning signs. Never stop a mood stabilizer suddenly without your doctor.
- Medication works best inside integrated care: treatment of both conditions together, with therapy, case management and an aftercare plan.
Table of Contents
- What mood stabilizers are and which ones are common
- Why dual diagnosis changes the medication picture
- What the evidence says, and what it does not
- How alcohol and drugs interact with mood stabilizers
- Lithium safety and monitoring
- Starting or adjusting medication during detox
- What integrated treatment looks like around the medication
- Questions to bring to your prescriber
- Our perspective
- Care at Connected Recovery
- When to get urgent help
- FAQ
- Sources
What mood stabilizers are and which ones are common
Mood stabilizers help manage the manic and depressive mood swings of bipolar disorder and can help keep those symptoms from coming back. Cleveland Clinic lists lithium, anticonvulsants such as valproic acid, lamotrigine and carbamazepine, and antipsychotics as the main groups. Lithium is the oldest of them: the same source notes the FDA has approved it as a mood stabilizer since 1970.
They are not fast. A Cleveland Clinic psychiatrist describes mood stabilizers as a mainstay of bipolar treatment that may take several weeks to reach their full effect. That timeline matters in a dual diagnosis setting, because early recovery from alcohol, opioids or stimulants is already a stretch of discomfort and mood instability. Expecting immediate relief from a mood stabilizer sets people up for frustration and for stopping too early.
A quick orientation to the groups:
| Group | Examples | What they are generally used for |
|---|---|---|
| Lithium | Lithium carbonate | Mania and long-term prevention of mood episodes |
| Anticonvulsants | Valproic acid (divalproex), lamotrigine, carbamazepine | Mood stabilization, with different strengths by drug |
| Antipsychotics | Quetiapine and others | Mania, mixed states, sometimes depressive episodes |
Which one fits you depends on your symptoms, your other medical conditions, other medications and, in dual diagnosis, your substance use pattern. That is a decision for a psychiatrist or other qualified prescriber, not something to work out from a table.
Why dual diagnosis changes the medication picture
Dual diagnosis, also called co-occurring disorders, means a mental health condition and a substance use disorder exist together. If you want the broader background first, our guide to understanding a co-occurring disorder diagnosis covers how it is identified.
With bipolar disorder, the two conditions tend to feed each other. Substance use can deepen both manic and depressive symptoms, according to SAMHSA's introduction to bipolar disorder and co-occurring substance use. Mood episodes, in turn, can drive drinking or drug use. Treating only one side usually leaves the other to pull the person back.
Three practical consequences follow for medication:
- Symptoms are harder to read. Intoxication and withdrawal can look like mania, depression or anxiety. A prescriber often needs a period of stability, and a clear history, before judging how well a mood stabilizer is working.
- Interactions matter more. Substances can change drug levels or add sedation, covered below.
- Adherence is part of relapse prevention. Integrated Group Therapy materials advise that not taking bipolar medication raises the risk of substance use relapse, per the same SAMHSA document.
What the evidence says, and what it does not
Honest answer first: there is no single best mood stabilizer for people who have bipolar disorder and a substance use disorder. The SAMHSA introduction states that research on medications effective for both disorders is limited. In one study, divalproex sodium combined with lithium as maintenance treatment was associated with reduced alcohol consumption, while studies of quetiapine for alcohol use disorder have reported mixed results (SAMHSA).
The 2023 VA/DoD guideline goes a step further. It finds insufficient evidence to recommend for or against a specific medication or psychotherapy for people with bipolar disorder and co-occurring substance use disorder. The same guideline recommends a collaborative care model and says its recommendations take patient values and preferences into account.
What does that mean for you?
- Mood stabilizers are still used to treat the bipolar disorder itself, which is the condition they have the strongest evidence for.
- Medication for the substance use disorder, where one exists (for example, for opioid or alcohol use), is a separate decision. See our page on medication assisted treatment.
- Because the data are thin, close follow-up matters more than any brand name. The best plan is the one a team adjusts as it learns how you respond.
Non-drug options are part of the same conversation for some people. One example is transcranial magnetic stimulation, discussed in this overview of TMS for bipolar depression. Whether any such option suits you is a question for your treating psychiatrist, especially with a substance use history.
How alcohol and drugs interact with mood stabilizers
This is the part many people never hear until something goes wrong. According to the SAMHSA bipolar and co-occurring substance use resource:
- Marijuana can cause a dramatic, potentially toxic increase in lithium levels.
- Alcohol combined with atypical antipsychotics may cause extreme central nervous system depression and significantly impair psychomotor functioning, meaning coordination and reaction.
- Substance use in general can deepen manic and depressive symptoms, which can make the medication look like it is failing when the problem is what is happening around it.
SAMHSA's general guidance on bipolar disorder also lists avoiding alcohol and other drugs, a consistent sleep schedule, limiting caffeine, eating well and regular exercise as habits that help manage symptoms (SAMHSA). None of these replaces medication. They make it work better.
If you are still using, tell your prescriber exactly what, how much and how often. A prescriber cannot adjust for a risk they do not know about, and honest disclosure is a safety step, not a confession.
Lithium safety and monitoring
Lithium is effective, and it is also the mood stabilizer with the narrowest safety margin, so monitoring is not optional. The FDA label for lithium says serum concentrations of 1.5 mEq/L or higher are toxic, and that this sits close to the 0.8 to 1.2 mEq/L therapeutic range used for acute mania (FDA label).
What monitoring usually involves
Per the same label:
- Before starting: evaluation of kidney function, vital signs, electrolytes and thyroid function.
- Blood level testing about 12 hours after the previous dose, then regular monitoring.
- Rechecks after a dose change, a change in another medication, a marked change in strenuous physical activity, or a new medical illness.
- Clinical judgment as well as numbers: the label states serum lithium concentrations alone are not sufficient for evaluation, and both clinical and laboratory analysis are needed.
Daily habits that protect you
The label notes lithium can cause low sodium (hyponatremia). It advises a normal diet, including salt, and fluid intake of 2,500 to 3,000 mL, at least during initial stabilization. Heavy sweating, vomiting, diarrhea and dehydration are the situations where levels can drift, which is one reason detox and early recovery need medical supervision when lithium is part of the plan. Ask your prescriber what applies to you before changing your fluids or salt intake.
Warning signs of toxicity
The label tells clinicians to watch for tremor, lack of coordination, ataxia, confusion and seizures. If you notice these in yourself or someone else on lithium, treat it as urgent (see the section on urgent help below).
Starting or adjusting medication during detox
Detox is a medically sensitive window. Withdrawal from alcohol or sedatives can be dangerous by itself, and dehydration and electrolyte shifts complicate lithium. Mood symptoms can also surface or intensify as substances leave the body. This is why people with a bipolar diagnosis are better served by medically supervised detox where nurses and physicians can observe both withdrawal and mood, rather than by trying to quit alone.
Timing of medication decisions varies. Some prescribers continue a stable regimen through detox, others adjust it, and some wait until withdrawal settles to judge baseline mood. Do not make that call yourself. Do not stop a mood stabilizer to "feel clear" before or during treatment. SAMHSA's guidance is that people should not stop taking medication without their doctor's guidance, and that long-term, continuous treatment can reduce the severity and frequency of mood swings (SAMHSA).

Low mood after detox is common and deserves its own plan. Our clinician's safety-first plan for depression after detox walks through what to watch for.
What integrated treatment looks like around the medication
Integrated care treats substance use and mental disorders at the same time rather than in sequence. SAMHSA's treatment guidance describes multidisciplinary teams that discuss pharmacotherapy, offer it when appropriate, and monitor it for safety, adherence and response. Clients may also receive several formats of treatment: individual, group, family and peer support (SAMHSA).
The same guidance describes team-based assertive community treatment and integrated case management, where a case manager with a low caseload helps people meet basic needs and reach community services. That is the practical glue: appointments kept, prescriptions filled, labs drawn, housing and work sorted.
Therapy has its own evidence. In one study cited by SAMHSA, participants in Integrated Group Therapy, which addresses bipolar disorder and substance use together, were more likely than those in group drug counseling to achieve abstinence and to be both abstinent and free of mood episodes in the final month of treatment (SAMHSA). Medication and therapy are partners, not alternatives.
For people who also manage anxiety, see how anxiety and addiction treatment fits together, and why mental health treatment helps you stay sober.
If you want a whole-person view of recovery, our guide to holistic addiction treatment explains the supportive pieces around clinical care. And because medication does not end at discharge, it is worth understanding the continuum of care so prescriptions, labs and therapy carry over.

Questions to bring to your prescriber
If you or a family member is starting or reviewing a mood stabilizer in dual diagnosis, these questions get to the heart of it:
- Which condition is this medication targeting, and how will we know it is working?
- How do my current or past substances interact with it? Be specific: alcohol, cannabis, opioids, stimulants, sedatives.
- What blood tests do I need, how often, and who orders them?
- What should I do if I vomit, cannot drink fluids, or start a new medication?
- What happens to this plan when I leave residential care? Who is the next prescriber?
- Which warning signs mean I should call you, and which mean I should go to the emergency room?
Write the answers down. Families helping a loved one can ask to attend the appointment when the patient agrees.
Our perspective
In our experience, the most common mistake with medication in dual diagnosis is treating it as a stand-alone fix. A mood stabilizer can steady the illness underneath, but it cannot do the work of detox, therapy, routine and support.
That is why we keep Connected Recovery intentionally small, at 12 beds. With so few clients, clinicians notice the small shifts: a night of poor sleep, a change in appetite, irritability that was not there yesterday. In a mood disorder, those details are the early signal, and they are easy to miss in a large facility.
We believe the right order is stabilize safely, assess both conditions, and then build a long-term plan. Medical supervision around the clock makes the first step safer, and integrated dual diagnosis care keeps the mental health side from being an afterthought.
If you are afraid that treatment means losing control of your medication or your privacy, ask us how we handle both. A good program should answer plainly.
Jim
Care at Connected Recovery
Connected Recovery is a boutique, 12-bed residential facility in Van Nuys, Los Angeles, serving adults. We offer medically supervised detox, residential treatment, dual diagnosis treatment for co-occurring mental health disorders, medication assisted treatment, and aftercare planning, with 24/7 medical supervision and treatment plans built around the individual.
If you or someone you love needs detox or residential care and has a mood disorder alongside substance use, contact Connected Recovery to talk about admission. Our residential treatment program and our case management services help keep medication, appointments and recovery goals connected, and aftercare planning continues that work after discharge. To discuss your own situation, reach out through our site.
When to get urgent help
Mood stabilizers are safe for many people when monitored, but some situations cannot wait for the next appointment.
Call 911 or go to the nearest emergency room for suspected overdose or lithium toxicity. The National Library of Medicine's MedlinePlus advises calling emergency services or poison control when someone has overdosed or has toxicity (MedlinePlus). Signs from the FDA label include tremor, loss of coordination, confusion and seizures. In the US, Poison Control is reachable at 1-800-222-1222.
Call or text 988 if you or someone you know is having thoughts of suicide or a mental health crisis. The 988 Suicide & Crisis Lifeline offers 24/7, judgment-free support.
Call your prescriber the same day for new severe sleeplessness with racing thoughts, a sudden crash in mood, vomiting or diarrhea that prevents you from keeping fluids down while on lithium, or a relapse into heavy drinking or drug use while on medication. Do not wait to see whether it passes, and do not stop the medication on your own.
FAQ
Can you take mood stabilizers if you are in recovery from addiction?
Yes. Mood stabilizers treat bipolar disorder and are commonly part of a recovery plan when both conditions are present. The prescriber needs a complete picture of your past and current substance use so they can choose a medication and monitor it safely. Never stop one without medical guidance.
Is there a mood stabilizer that also treats alcohol or drug addiction?
Not reliably. SAMHSA notes research on medications effective for both disorders is limited, with one study linking divalproex plus lithium to reduced drinking and mixed results for quetiapine. Medications for alcohol or opioid use disorder are a separate decision from your mood stabilizer, made by your treatment team.
Can I drink alcohol or use cannabis while on a mood stabilizer?
It is risky. Marijuana can sharply raise lithium levels toward toxicity, and alcohol with atypical antipsychotics can cause extreme sedation and impaired coordination. SAMHSA also lists avoiding alcohol and other drugs among habits that help manage bipolar symptoms. Be open with your prescriber about any use.
How long do mood stabilizers take to work?
Often several weeks to reach full effect, according to Cleveland Clinic. Dose adjustments and blood tests are normal in that period. Report side effects instead of stopping, since your prescriber may be able to change the dose or the drug.
Do I need blood tests on a mood stabilizer?
For lithium, yes: the FDA label calls for kidney, thyroid and electrolyte evaluation before starting and regular serum level checks after. Other mood stabilizers have their own monitoring, so ask your prescriber which tests apply to your medication.
Sources
- Mood Stabilizers: What They Are, How They Work and Side Effects, Cleveland Clinic
- Mood Stabilizers vs. Antipsychotics for Bipolar Disorder, Cleveland Clinic
- An Introduction to Bipolar Disorder and Co-Occurring Substance Use Disorders, SAMHSA
- VA/DoD Clinical Practice Guideline for Bipolar Disorder, Quick Reference Guide, 2023
- Lithium prescribing information, FDA label
- Substance Use Disorder Treatment for People with Co-Occurring Disorders, SAMHSA
- What is Bipolar Disorder?, SAMHSA
- Lithium toxicity, MedlinePlus
- 988 Suicide & Crisis Lifeline, SAMHSA
- TMS for Bipolar Depression: What the Evidence Says